
Weeks 1–2
Pain
Make touch tolerable again.
Desensitization and gentle hands-on care start where your limb can actually cope, not where a protocol says it should be.
What We Treat
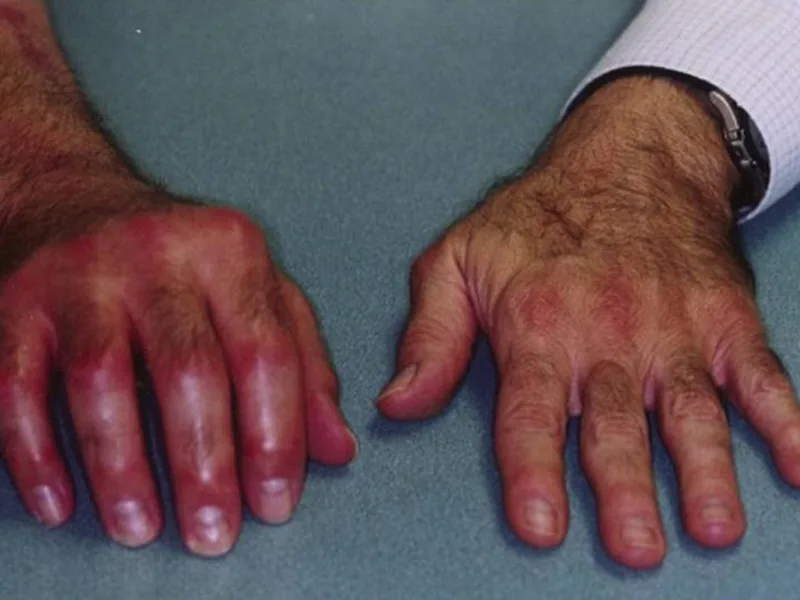
Burning pain far out of proportion to the injury. A limb that cannot stand a sock. Complex regional pain syndrome is real, it is understood, and how it gets treated matters enormously.
Sound Familiar?
Two or more? With CRPS, the sooner someone takes it seriously, the more you have to work with.
Why It Happens
Something happened first. A fracture, a sprain, a surgery, sometimes almost nothing. The tissue healed. The alarm system did not switch back off. Nerves, blood flow and the immune response stay locked in a loop, and the brain’s map of that limb goes blurry. That is why a light touch can burn, and why the limb can feel like it belongs to someone else.
So the evaluation is careful, cause-first, and led by someone who works in this territory. Natalie Johnston is a Fellow in Pain Sciences and a Therapeutic Pain Specialist with 24 years of experience, and complex and chronic pain is her stated specialty. We find what your limb tolerates today, what it is guarding, and where the map has gone quiet. Then we work at that edge, never past it.
You have already read everything, and you have probably already been somewhere that pushed too hard, too fast. That is exactly the kind of patient who does well here.
The Honest Truth
Nobody regrets starting too early. Plenty of people tell us they wish they had come in sooner.
How We Fix It
Every plan has an endpoint. Here’s what the four phases look like for a limb that is stuck on alarm.
Weeks 1–2
Pain
Desensitization and gentle hands-on care start where your limb can actually cope, not where a protocol says it should be.
Weeks 2–6
Prime
Graded motor imagery, mirror work and small ranges of motion give the brain clear signals from that limb again.
Weeks 6–10
Perform
Weight bearing and real use return in graded steps, so function grows without tripping the alarm.
Weeks 10+
Prevent
You leave able to spot an early flare and walk it back down yourself, using a plan you have already practiced here.
Natalie knows her stuff! She understands how painful works, how it affects your body and life. She knows how to help you help yourself to get your life back.
Karmen W. · Verified Google review
Today: even a sleeve on that limb is more than you can take
The goal: more use of it, fewer flares, and a limb that feels like yours
Questions, Answered
Aggressive therapy can absolutely flare CRPS, so that fear is legitimate and we treat it as legitimate. We go the other direction. We find what your limb tolerates today, work just under that line, and change the dose the moment it is too much. You are one-on-one with a licensed physical therapist every visit, so nobody is guessing at your tolerance.
We are not going to promise you that. CRPS is a condition you learn to manage, and management can look like a great deal: more use of the limb, flares that are shorter and further apart, sleep back, and a clear understanding of what your body is doing. That is what we build toward, and we say so up front.
A full plan for CRPS runs through all four phases, Pain, Prime, Perform, and Prevent, and how long that takes depends on how long the limb has been guarded. Either way, you get a plan with an endpoint: you’ll always know which phase you’re in and what’s left, not an open-ended string of appointments.
Book Your Visit
Request a time and a real person calls you back. No phone tree. No ‘someone will reach out.’ Just a plan.
4.9 · 79 Google reviews
Typical response: under 2 business hours
Step 1 of 5
That’s the hard part done. We’ll call during business hours to lock in your time.
Visit Us